Clarify what each contract pays
Resolve payer products, Medicare base years, carveouts, and effective dates. See which contracts pass Medicare changes through, which remain fixed, and the annual revenue impact.
 Contact us
Practice financial intelligence
Plan for payment changes, negotiate with market evidence, and identify likely underpayments. Bring surgery, imaging, injections, therapy, and ancillary revenue into one contract and service-line view.
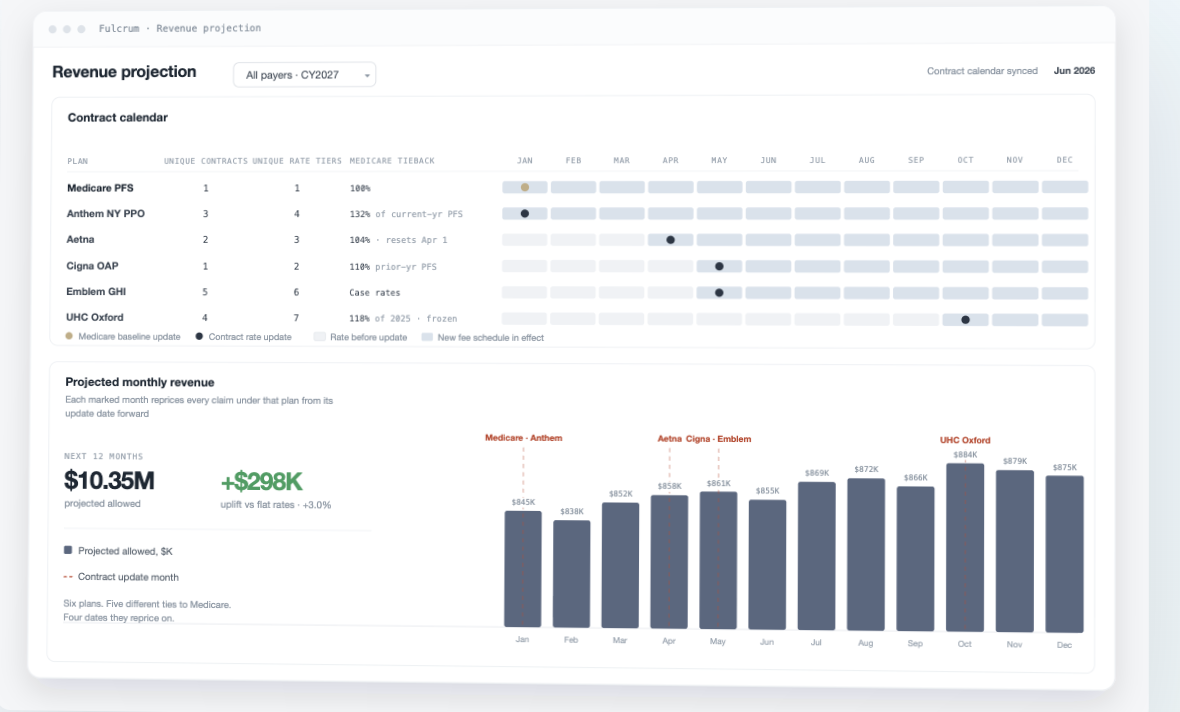
Financial visibility for Orthopedic Surgery
Fulcrum connects reimbursement terms to actual volume across surgery, office procedures, imaging, and therapy so leaders can compare payer performance and service-line revenue in one place.
Fulcrum Light
Start with a claims export and your contract set. Fulcrum adds payer-published in-network rates to model your payment exposure and compare your position in the market. No EMR integration required.
Resolve payer products, Medicare base years, carveouts, and effective dates. See which contracts pass Medicare changes through, which remain fixed, and the annual revenue impact.
Forecast claim-line changes by service, location, and provider. Toggle proposed policies, compare scenarios, and save analyses to rerun when your data changes.
Compare rates with other groups contracted with the same payer, by insurance product. Model proposals on your volume and use monthly rate history to inform contracting and growth decisions.
Check claims against contract terms and payer-published rates, then review EOB evidence to screen false positives. Continuous service includes a monthly report, appeal evidence, and next steps.
What becomes answerable
CY 2027 proposed PFS
A national specialty average is useful context, not a practice forecast. Your result depends on your codes, volume, locality, sites of service, and Medicare-linked contracts.
Proposed change in RVU-based allowed charges, before the separate conversion-factor adjustment.
CMS's own reconciliation table (Table D-B5) puts orthopedic surgery at -5.8% for 2027. That figure is the specialty-wide, volume-weighted change in total RVU-based allowed charges: the aggregate gain or loss across every code the specialty bills, before the separate conversion-factor cut.
Orthopedic Surgery bills about 47% of its Medicare dollars in the office (non-facility) setting. Fulcrum's reconstruction estimates the following changes by site of service:
| Site of service | Change | Allowed $ |
|---|---|---|
| Office (non-facility) | -5.8% | -$90M |
| Facility | -8.9% | -$155M |
All figures are national, hold 2025 utilization fixed, and exclude the separate conversion-factor adjustment. CMS proposes a 1.68% reduction for non-qualifying APM participants and a 1.19% reduction for qualifying APM participants. These adjustments are separate from the RVU-based changes shown above.
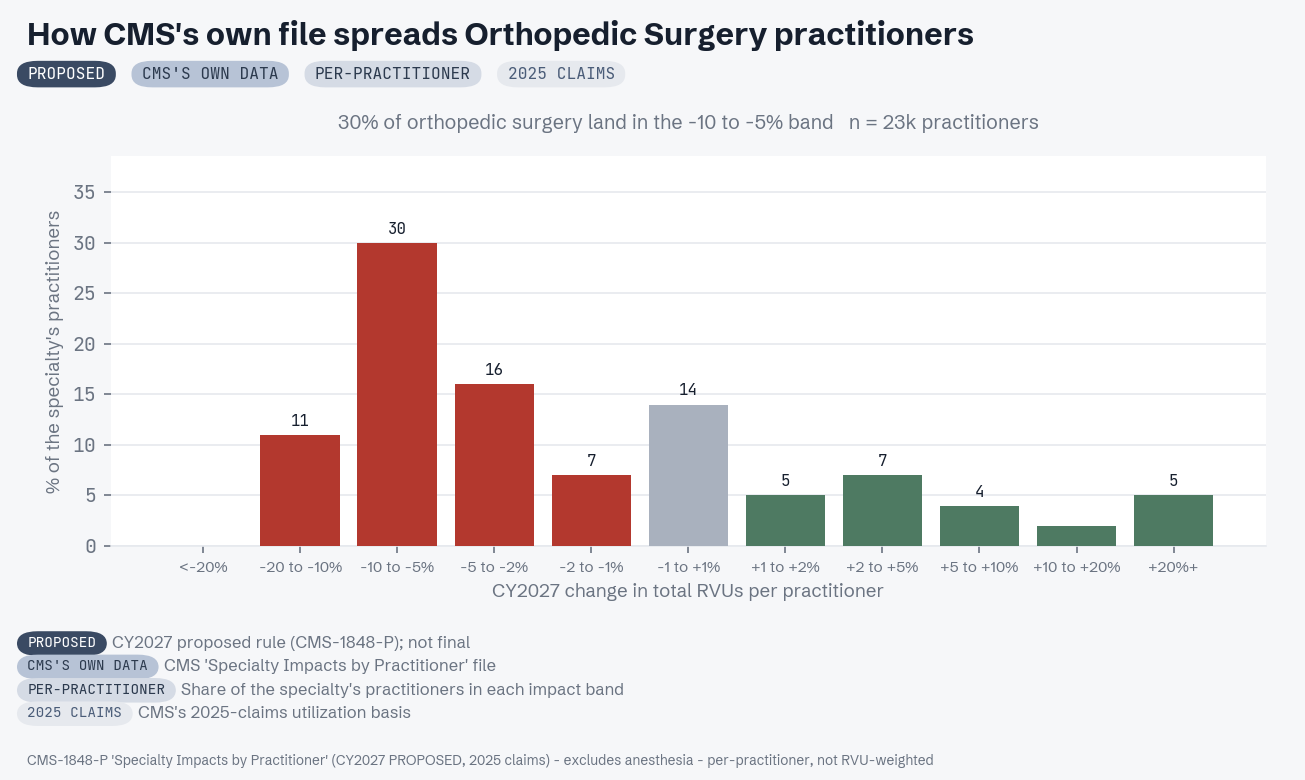
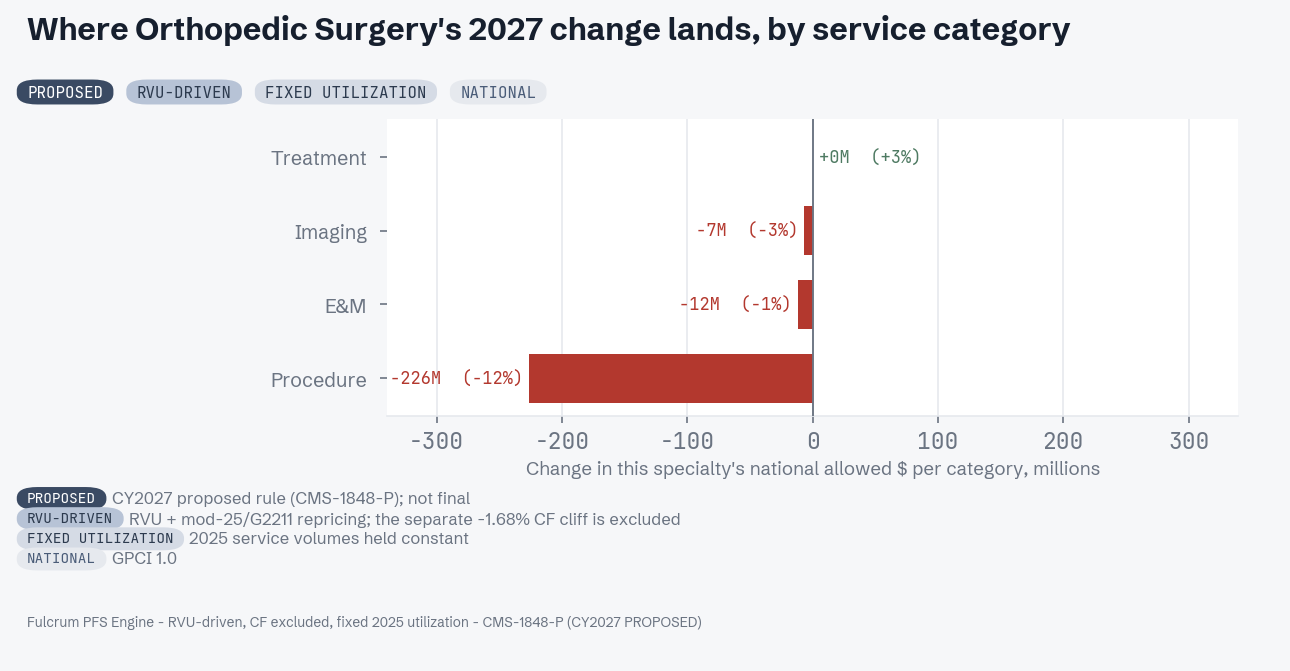
The charts exclude conversion-factor changes. The −1.68% adjustment noted in the category chart applies to non-qualifying APM participants; the proposed adjustment for qualifying participants is −1.19%.
The specialty average hides a wide spread, and CMS's own practitioner-level file proves it. 30% of orthopedic surgery practitioners land in the -10 to -5% band, and about 57% see a cut deeper than 2%. Where a practice lands is a question of service mix: the orthopedic surgery practices hit hardest are those with the heaviest major-joint arthroplasty volume; the office injection-and-visit practices move far less.
Practice-specific analysis
Choose a one-time analysis or continuous planning with Fulcrum Light. Both start with your claims and contracts; no EMR integration is needed.